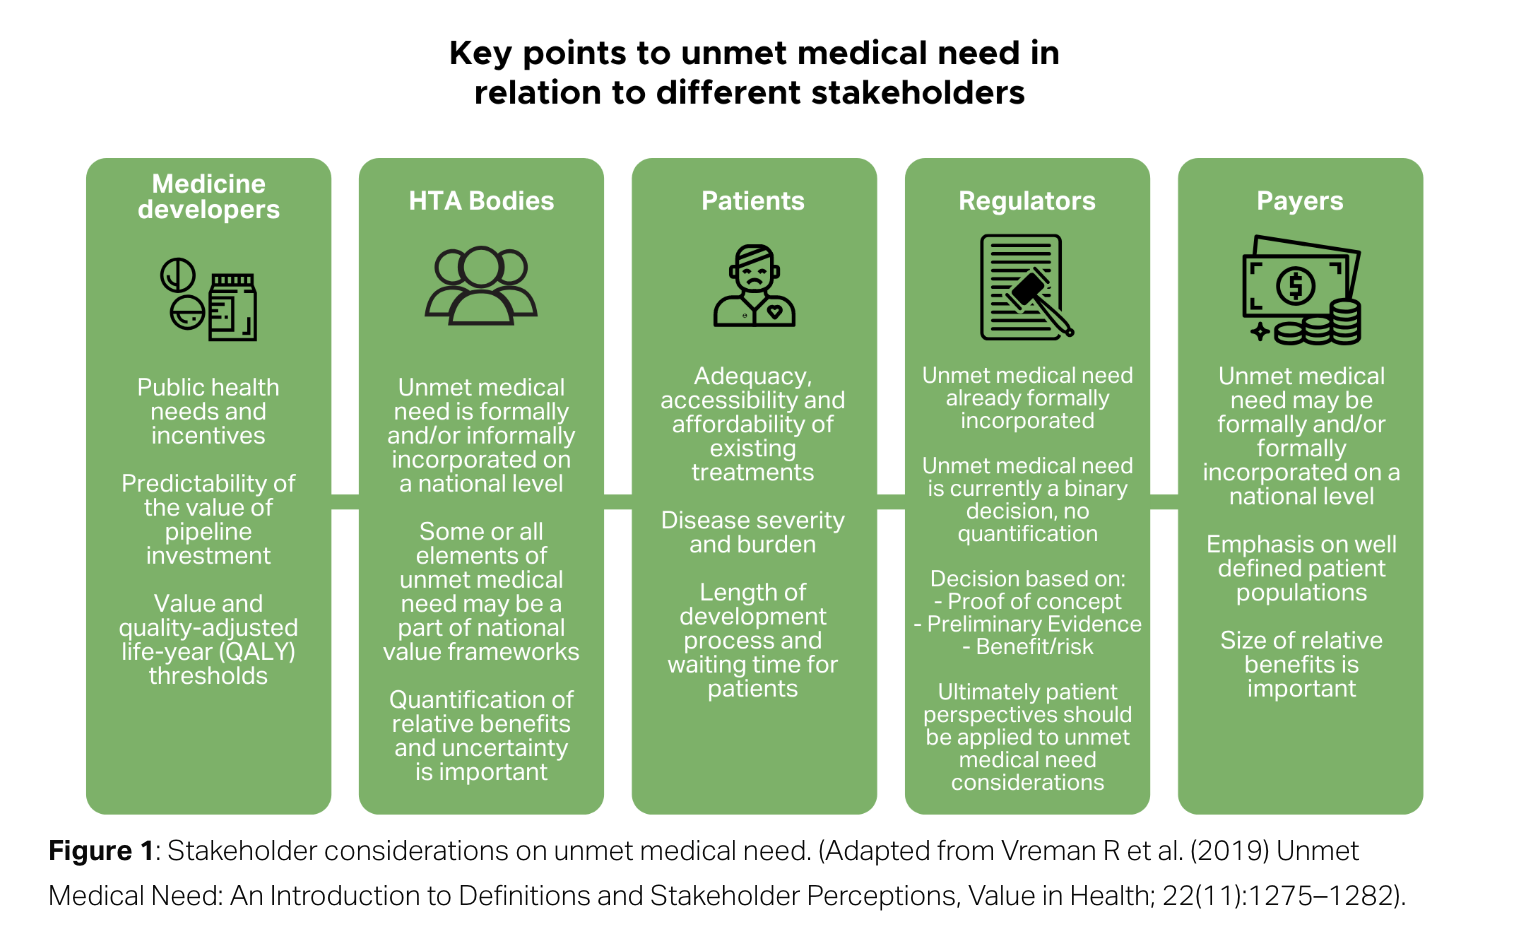
In Europe, the debate on Unmet Medical Need (UMN) is no longer just technical. It has become deeply political.
Over the last twenty years, the European regulatory framework has enabled extraordinary progress in rare diseases: from few therapies available to over 250 approved treatments. Yet, for the vast majority of people living with rare diseases, therapeutic options still remain limited.
The revision of European pharmaceutical legislation introduces, for the first time, a more structured definition of UMN and explicitly links incentives for innovation to the ability of new treatments to address still unmet needs. This is an important turning point.
But it is also a high-risk step.
In the coming months, the European Medicines Agency will be called upon to translate this definition into operational guidelines. This is where the decisive game will be played. Because the way UMN is interpreted will not only determine regulatory criteria, but will also steer investment, research and, ultimately, patients’ access to innovation.
If UMN is defined too narrowly, limiting it, for example, to the mere absence of treatments or to traditional clinical endpoints, we risk penalizing areas that are fundamental for patients, such as quality of life, cognitive functioning or the reduction of treatment burden.
Phenylketonuria (PKU) is an emblematic case. Despite decades of progress, living with PKU still means facing complex daily management: a very strict diet, continuous monitoring, and significant psychological and social impacts. It is not a "solved" disease.
Reducing the concept of unmet need to the mere availability of a therapy means ignoring this reality.
For this reason, it is essential that future UMN guidelines reflect the complexity of rare diseases and patients’ experiences. In particular, three principles should guide its definition:
Value outcomes that matter to patients, including quality of life, mental health and treatment burden
Recognize the evolution of need throughout the entire lifespan, avoiding static approaches or those limited to specific stages of the disease
Support incremental progress as well, where significant levels of morbidity persist
As a leader committed every day to promoting access to innovation in rare diseases, I clearly see how decisive this choice will be.
This is not just about defining regulatory criteria. It is about taking on a collective responsibility toward a patient community that, too often, continues to live with still unmet needs, despite the existence of therapeutic options.
If we truly want to put the patient at the center, we must have the courage to recognize that “treating” does not necessarily mean “meeting the need.” And that innovation, to be relevant, must concretely improve people’s lives, not just clinical parameters.
For this reason, it is essential that institutions, industry, the scientific community and patient associations work together to build a definition of UMN that is forward-looking, inclusive and sustainable.
As PTC Therapeutics, we are ready to do our part. With responsibility. With rigor. But also with the conviction that Europe can, and must, continue to be a global benchmark in innovation for rare diseases.
Because, ultimately, this is not just a policy choice. It is a choice of vision. And of values.
Riccardo Ena, PTC Therapeutics